Overview
The Center has been an active partner in collaborative and transdisciplinary global research since it was established in 2018.
This page provides an overview of archived research projects. For more information about these projects, please email us at cirgh@sph.cuny.edu.

The Health Equity & Access to Care (HEAC) Project
From 2022-2024, we collaborated with the NYC Department of Health and Mental Hygiene on the Health Equity and Access to Care (HEAC) project, which sought to better understand New Yorkers’ experiences accessing healthcare in hospitals in New York City (NYC). The results were shared with the health department to inform NYC healthcare recommendations to better serve all New Yorkers.
COVID-19 and Big Cities
To explore exacerbating and mitigating factors of large urban areas on migrants’ vulnerabilities during the COVID-19 pandemic, CIRGH conducted a systematic review of peer-reviewed studies published between 2020-2022 and focused on migrants in urban areas with a population >500.000.
After screening 880 studies, 29 studies were included and categorized within the following thematic framework:
- Underlying structural inequities
- Governance and economic structure
- Urban design
- Engagement of civil society organizations (CSOs)
Exacerbating factors include pre-existing inequities (e.g. unemployment, financial instability, and barriers to healthcare access), exclusionary government responses (e.g. relief funds or unemployment benefits), and residential segregation. Mitigating factors include the engagement of CSOs and the implementation of innovative governance strategies (e.g. e-governance and use of teleservices). We recommend increased attention to pre-existing social inequities faced by migrants, inclusive governance strategies, and partnerships between government and CSOs to improve the design and delivery of services to migrants in large urban areas. More research is needed on how urban design can be utilized to mitigate the COVID-19 impacts on migrant communities. The factors identified in this systematic review should be considered as part of migrant-inclusive emergency preparedness to address the disproportionate impact of these crises on migrant communities.
Study Design
Systematic Literature Review
Search Terms
(COVID-19 OR covid OR corona OR coronavirus OR sars-cov OR sars-cov-2) AND (migrant OR migrants OR Immigrant* OR Immigration OR newcomer* OR “asylum seeker*” OR asylee* OR “displaced person” OR “displaced people” OR “foreign born” OR “foreign worker*” OR “foreign domestic worker*” OR refugee* OR undocumented) AND (city OR urban OR cities OR metropolitan OR metropolis OR megacity OR suburb*)
Methodology
We conducted a systematic literature review in PubMed, Web of Science, and the WHO COVID-19 database, which generated 880 results. Inclusion criteria encompassed English, peer-reviewed literature with a focus on COVID-19 effects on migrants in cities with populations > 500,000. Both quantitative and qualitative study designs were included. Due to the newly emerging topic, we also included review papers, commentaries, and perspective pieces. Exclusion criteria included study protocols, validations studies, and clinical studies focusing on additional comorbidities.
After screening titles, abstracts, methodologies, and full texts, 29 studies were included. Eligibility disputes were solved by a consensus decision among all reviewers. Eligible studies were then coded according to the following information: Methodological quality, research question, study design, study setting, population of interest, age and number of participants, main findings, limitations, and discussion. The methodological quality was assessed with the Joanna Briggs Institute Critical Appraisal Checklist according to study type.
In line with evidence of urban factors influencing the COVID-19 impact and the main themes of eligible studies of our systematic review, we developed a thematic framework with four categories reflecting the main exacerbators and mitigators of COVID-19 impact on migrant communities in large urban areas: 1) Underlying structural inequities, 2) governance and economic structure, 3) urban design, and 4) engagement of CSOs. Each study was classified according to these themes based on their main key takeaways.

Key Study Findings
- Underlying socioeconomic inequities have exacerbated the impact of the pandemic on migrant groups in large urban areas. Unless these issues are addressed, migrants and other vulnerable populations will experience the same disproportionate impacts during the next pandemic or other health emergencies.
- Government responses, relief funds, and benefits often exclude migrants, further exacerbating inequities and disproportionate impacts. Governance strategies make a difference in mitigating the impact of COVID-19 on vulnerable groups, including migrants. Examples of effective strategies include: inclusive relief measures that provide migrants with basic financial and social support; suspension of policies and regulations that invoke fear and avoidance of services, particularly among undocumented migrants; support of local CSOs to fill gaps and complement municipal services; and e-governance initiatives that take into account the technology and connectivity challenges faced by migrant communities.
- The design of large urban areas can impact the exposure of vulnerable groups to health threats. In the case of COVID-19, urban areas with high levels of residential segregation place migrants and other vulnerable groups far outside the city center, therefore risking higher levels of infection among those groups. This is due to overcrowding in these neighborhoods, as well as the length and type of journeys people take to arrive at their places of employment.
- CSO engagement is a mitigating factor for the impact of COVID-19 among migrant groups in large urban areas. If adequately supported and financed, CSOs fill service gaps, bridge cultural divides, and strengthen community engagement in ways that protect migrant groups from exposure and increase access to preventive information and services.
Maternal and reproductive health in western new york
Buffalo and the surrounding area have a large, diverse and increasing migrant population with diverse cultural and linguistic backgrounds leading to diverse maternal and reproductive healthcare needs.
While there appears to be a robust foundation of local, community-based organization (CBO) providers serving migrants in Buffalo, there appears to be less emphasis on health and almost none focused on maternal and reproductive health (MRH) relative to services like housing, legal representation, education, economic support, and language/interpreter services.
Data systems strengthening
The Health Data Collaborative (HDC) provides a collaborative platform that leverages and aligns technical and financial resources to country-specific strategies and guidelines for collecting, storing, analyzing and using data to improve health outcomes.

Using a strong foundation of evidence and resources, the Health Data Collaborative achieves a measurable impact on health information systems strengthening in countries using three core strategies:
- coordination and alignment
- innovation and new technology
- capacity building
Together, these three areas contribute to greater alignment amongst donors and partners with national Monitoring and Evaluation plans, increase country capacity to introduce new technologies at a national and subnational level, and build sustained institutional capacity for data collection, reporting and use.

Health Data Governance Principles
Protect people, promote health value, and prioritize equity
The Digital Data and Governance Working Group, in collaboration with Transform Health, published the Health Data Governance Principles in 2024. The eight Principles consist of three interconnected objectives: Protect people, Promote health value and Prioritize equity. The Principles aim to bring a human rights and equity lens to the use of data within and across health systems with the orientation for delivery of Universal Health Coverage (UHC). The Principles provide adaptive user guides and toolkits based on industry to inform the development of health data governance frameworks and guidance that can be incorporated into national standards, legislation and organizational policies related to health data. The Principles have been endorsed by 97 organizations, governments and other stakeholders to date, including CUNY CIRGH.
Strengthening Surveillance of Pregnancy Outcomes
Understanding the distribution, strengths and limitations of available approaches used for health data collection is vital to ensure the appropriate surveillance strategy is utilized. The aim of this project was to develop guidance for low- and middle-income countries (LMICs) on safety surveillance in pregnancy.
This work involved coordinating across WHO departments to review previous or ongoing activities, activities developed in the context of COVID-19 and other planned activities identified by each WHO department within the WHO Interdepartmental Task Team. Key technical and operational guidance & reports, public data portals, registrar and systematic reviews, meta-analyses, and other original research were reviewed for indicators to identify the optimal data models to implement in LMICs based on data indicators currently collected by HMIS. The aim of this work:
- To translate evidence into clinical practice guidelines through the standardized diagnosis of key selected neonatal and perinatal outcomes.
- Reviewing and updating guidelines based on the projected 2023 pilot of the optimal data models implementation, based on the findings of the Task Team. This process was conducted to assess changes in recording and reporting elements related to safety monitoring of pregnancy interventions in selected countries

Stakeholders & Information Systems
Reliable, quality health information is the foundation of measurement and decision making in the health sector that can help improve the quality and coverage of health services, aid in policy development, support program implementation, and increase the likelihood that a well-trained health work force.
It is of increasing importance to understand stakeholder engagement in global norm setting processes, particularly influential HMIS stakeholders whose views have not been well documented. The strategy for this research involved participant observation of global consultative processes at the World Health Organization (WHO) regarding member states’ development and use of health data, document review from members states participation in a series of consultative meetings and a stakeholder survey administer to in-country health management information system (HMIS) specialists, primarily from Ministries of Health, from Botswana, Eswatini, Kenya, Malawi, Nigeria, Tanzania, Uganda, and Zimbabwe.
Based on the research findings, the following recommendations were presented:
- Involve stakeholders regularly and systematically so that development efforts reflect in country user and decision maker perspectives.
- Address infrastructure investments needs with multisectoral engagement.
- Digitization strategies must recognize non digital environments or we risk leaving people behind.
- Discourage duplicative parallel systems, instead focus on data governance and coordination to better align national and global priorities.
- Promote broader data use through targeted capacity development that addresses end user data needs.

Improving National Health Management Information Systems
Stakeholder Views in Selected Sub-Saharan African Countries
Recommended Citation: Donaldson, Marie, “Improving National Health Management Information Systems: Stakeholder Views in Selected Sub-Saharan African Countries” (2021). CUNY Academic Works. https://academicworks.cuny.edu/sph_etds/74
Implementation Science Collaboration for Urban Health in East Africa
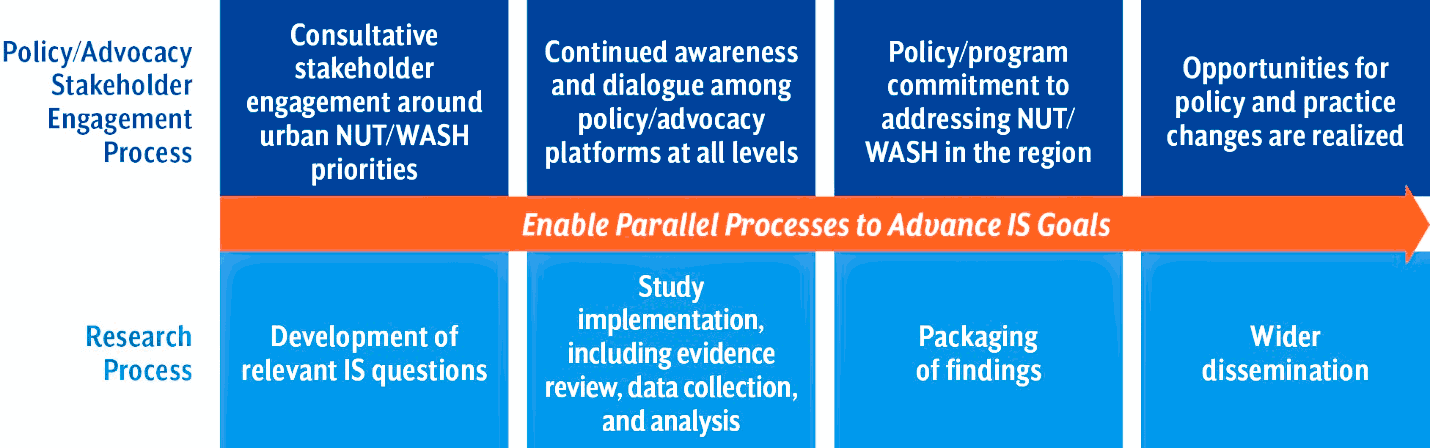
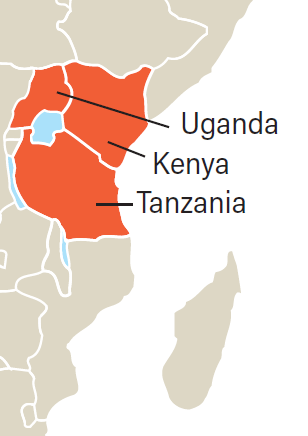
The three-Country Assessment of Nutrition and WASH Vulnerabilities Among the Urban Poor in East Africa assessment used desk review and case study methodology to identify and synthesize literature, polices, available data, strategies, partners, platforms, and contextual factors influencing child and adolescent health in poor urban areas of Kenya, Tanzania, and Uganda.
The country teams each used a similar design to allow for a cross-country synthesis of findings, which was guided by the UNICEF framework for undernutrition. While the situation differed across countries, there was a general dearth of urban-specific policies, data, evidence, and relatively few interventions targeting nutrition/WASH among poor populations. To learn more, see the cross-country briefs on this page. For country specific information, explore the information and briefs below.
Uganda

Although Uganda is rural, with only 18% urbanized land, it is among the most rapidly urbanizing countries in sub-Saharan Africa. According to World Bank indicators, 53.6% of Uganda’s urban population was living in slums as of 2015. To meet nutrition and WASH challenges, among others, the Ugandan government and partnering organizations have made progress developing policies and strategies that address the urban poor. The assessment findings highlight additional gaps and opportunities to use evidence to inform action.
Source: Uganda Country Brief
Kenya

Kenya’s urban population is rapidly increasing, with approximately 32% of the population residing in urban areas. This increase has put pressure on basic facilities such as water, sanitation, security, housing and transportation. In Nairobi, over half of the population resides in slums. The assessment findings reinforce the range of challenges facing poor urban children and adolescents. While there is relatively more evidence, data and a more supportive policy environment than in other countries in the region, opportunities remain to use information to inform action—especially for adolescents.
Source: Kenya Country Brief
Tanzania

Tanzania’s rapid rate of urbanization has resulted in a high proportion (60%) of people living in informal settlements. It is estimated that more than half of the population (55.40 to 63.12%) will live in an urban area by 2030. The drivers of rural-urban migration are employment opportunities and higher education, as well as rural youths being drawn to an urban lifestyle. To address nutrition and WASH challenges, the assessment findings identify gaps and opportunities to use evidence to inform action.
Source: Tanzania Country Brief